- Home
- Sleep Apnea Treatments
Sleep Apnea Treatment Paths: Right Type, Right Fit
When you're already exhausted, sorting through a full list of options can feel like too much. Take a breath — you don't have to figure this out alone. This is a researched treatment guide, based on what doctors generally agree on, to find the most effective and comfortable sleep apnea treatment for your type.

Treatment decision guide for beginners
Here's what this page helps you decide: which treatment is worth trying first, based on how your apnea shows up.
Start here — three questions to answer before anything else:
- What's driving your events? Obstructive (airway blocked), central (brain-signal related), or a mix — this shapes almost everything else.
- How severe is it, and when does it happen? Severity, and whether it's positional or REM-predominant (mostly during dream sleep), change what "first step" even means.
- What can you actually live with? Comfort, travel, claustrophobia, and jaw tolerance matter as much as the medical fit.
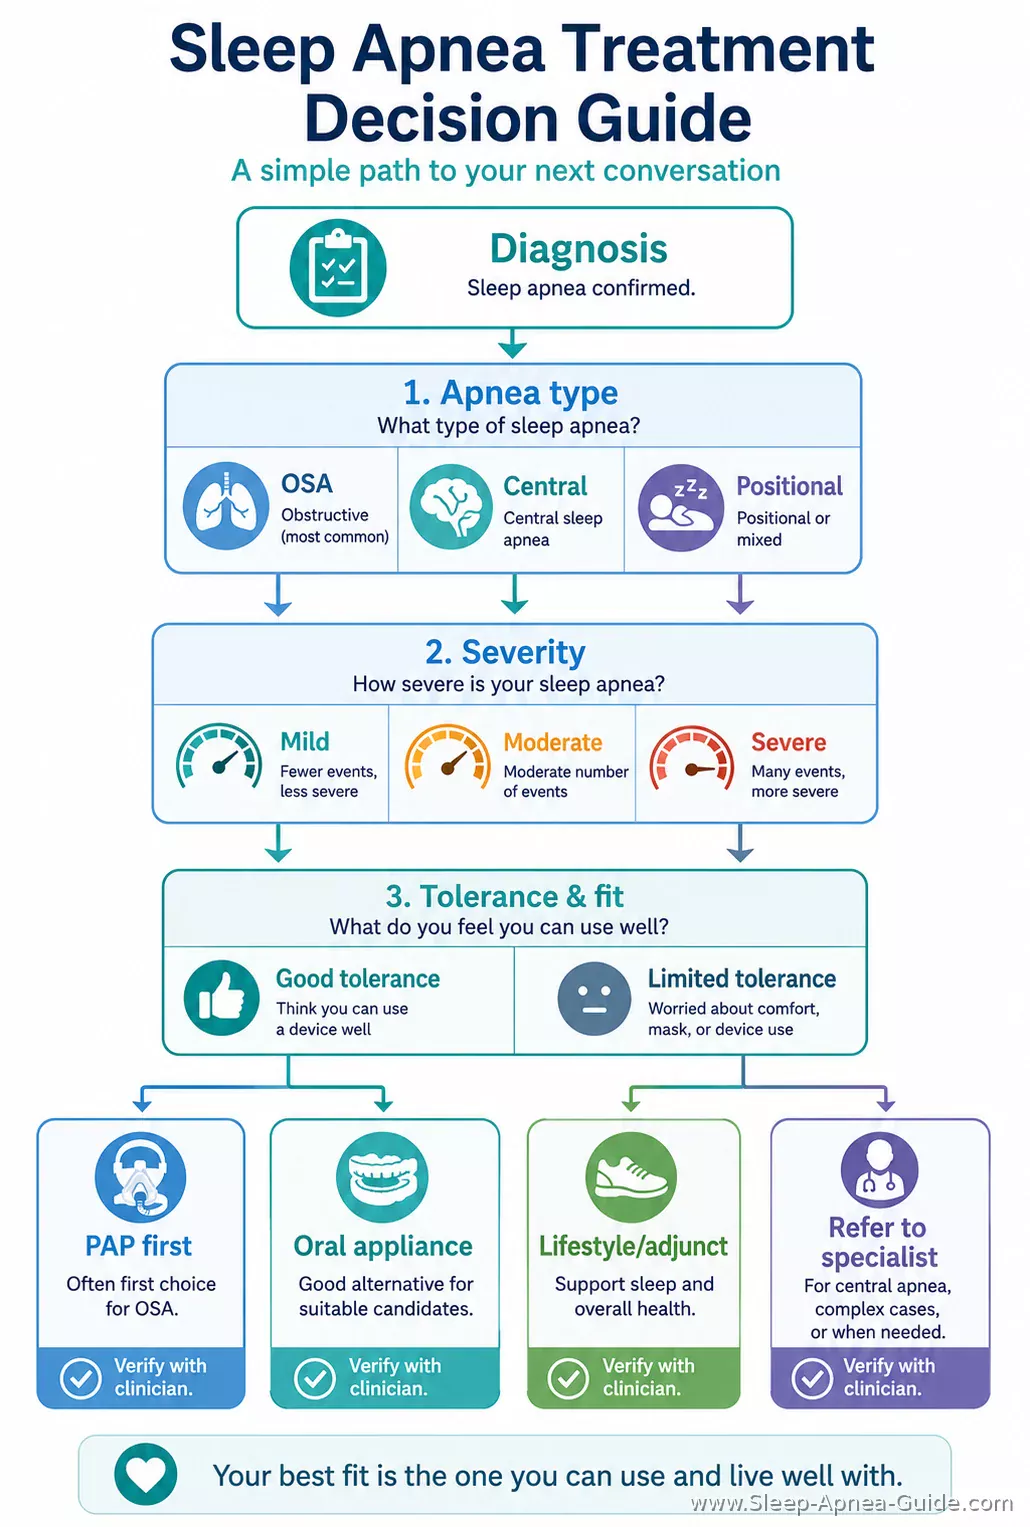
Your next step usually depends on:
- Obstructive events → PAP/CPAP is usually where the conversation starts. Guidelines from the American Academy of Sleep Medicine recommend positive airway pressure therapy for adults with obstructive sleep apnea who have excessive daytime sleepiness. [1]
- Central or mixed flags → a specialist typically looks at advanced PAP options. Central sleep apnea isn't covered by the standard adult obstructive sleep apnea PAP guideline — evaluation and treatment depend on the underlying cause, which is part of why it usually needs specialist input. [2]
- Positional or REM-predominant pattern → positional therapy or targeted adjustments may come first.
- Noticeable oxygen drops on your sleep study → this often shapes urgency and machine settings, even within PAP.
- Comfort concerns like claustrophobia, travel, or jaw tolerance → worth raising with your clinician early, not after months of struggling.
This is a research-based reference — always verify your specific plan with your clinician.
Ready to see what usually comes first for your pattern? Scroll down to Treatments by apnea type.
Sleep apnea treatment options
Understanding your sleep apnea treatment options helps you and your doctor find a path you can stick with.
These are the main treatment paths for sleep apnea:
- Primary — come up first in most conversations (PAP/CPAP, and oral appliances for some)
- Supportive — work alongside a main therapy (positional therapy, weight-related changes)
- Specialist-led — require screening (surgery, nerve stimulator implants)
PAP/CPAP Therapy (First-line where appropriate)
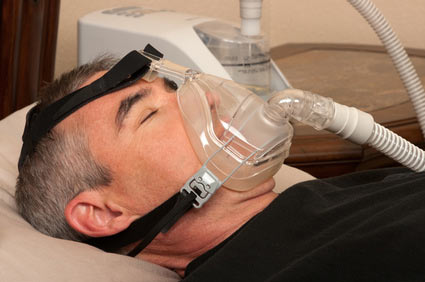
- What it is: Positive Airway Pressure (PAP) therapy uses a bedside machine and mask to deliver pressurized airflow that helps keep the airway open during sleep. CPAP (Continuous PAP) is the most common type you'll hear about.
- Who it tends to fit: Many patients with obstructive or mixed patterns who need effective, standard airway support.
- Especially worth discussing if: your sleep study shows obstructive or mixed events.
- Also worth raising if: you're unsure a nightly mask and machine fit your routine or travel life.
- What to expect: You'll need time to adjust — to mask comfort, air pressure, and routine machine upkeep. Real adjustment time before it feels normal is common.
- What to verify with your clinician: "What would you consider a successful adjustment period, and when should I check back in if it's not working?"
Oral Appliances (Situational / First-line for some)

- What it is: a custom-fitted dental device worn at night that repositions the jaw or tongue to help keep the airway open.
- Who it tends to fit: Those with mild to moderate obstructive apnea, or those who can't tolerate CPAP therapy.
- Especially worth discussing if: your sleep study shows mild to moderate obstructive apnea.
- Also worth raising if: you've given CPAP an honest trial and it hasn't worked for your routine, comfort, or travel life.
- What to expect: A custom dental device that gently shifts the jaw forward. It's portable and travel-friendly. Expect an adjustment period and ongoing dental check-ins.
- What to verify with your clinician: "What would rule this option out for me — jaw health, TMJ history, or something else?"
Lifestyle and Adjuncts (Supportive)
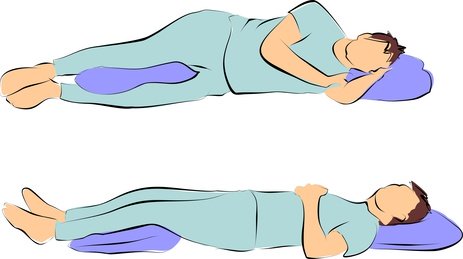
- What it is: supportive steps — like positional therapy, weight-related changes, or throat exercises — that can improve results alongside a primary therapy, but don't replace it for many moderate to severe cases.
- Who it tends to fit: People who want to support their main therapy with positional changes or targeted health habits.
- What to expect: Gradual, supportive improvements. These rarely replace primary medical devices for moderate to severe cases. Guidelines place weight reduction inside a comprehensive treatment plan for adults with OSA and overweight or obesity, rather than as an automatic replacement for PAP or other primary therapy. [3]
- What to verify with your clinician: Confirm which supportive habits safely go alongside your main treatment plan.
Surgery (Specialist-led / Situational)
- What it is: procedures that target specific anatomical blockages in the airway, evaluated and performed by an ENT or sleep surgery specialist.
- Who it tends to fit: Patients with specific anatomical blockages, or those who have tried standard non-invasive therapies without success. Guidelines generally place surgical referral discussions after CPAP intolerance or non-acceptance, and separately support discussing bariatric surgery referral for adults with more severe obesity who can't tolerate CPAP. [4]
- What to expect: A specialist evaluation followed by a recovery period. Comfort and ease of living improve if the airway is successfully cleared.
- What to verify with your clinician: Discuss surgical risks, recovery timelines, and long-term success rates for your specific anatomy. Different procedures target different anatomy — nasal surgery addresses nasal blockage and is generally positioned as a way to improve breathing and PAP tolerance rather than a stand-alone fix, tonsillectomy addresses enlarged tonsils, and procedures like uvulopalatopharyngoplasty or maxillomandibular advancement target different levels of airway collapse. [4][5][6]
Implant-based Options (Specialist-led)

- What it is: a surgically placed device — often a nerve stimulator — that helps keep the airway open during sleep; eligibility is screened through a specialist evaluation.
- Who it tends to fit: Moderate to severe obstructive patients who can't tolerate CPAP and meet certain anatomy-based requirements. FDA labeling for this type of nerve stimulator covers adults 22 and older with moderate to severe obstructive sleep apnea who can't use or tolerate PAP, and excludes people whose central or mixed events make up more than a quarter of their total events. [7]
- What to expect: A surgically implanted nerve stimulator, turned on at night. It can mean you no longer need a mask. Getting to this point typically involves surgery, a healing period before the device is turned on, and gradual adjustment over time, along with follow-up sleep testing to fine-tune the settings. [8]
- What to verify with your clinician: Confirm your eligibility through a drug-induced sleep endoscopy (a sleep study done under light sedation) and discuss surgical requirements. A related but separate device — approved for moderate to severe central sleep apnea rather than obstructive — works by stimulating a different nerve, which is why central sleep apnea candidacy follows its own separate pathway. [9]
Where to go next (based on your sleep study report):
If you're obstructive (OSA) and not sure where to begin → start with the Mild obstructive apnea treatment plan.
- If your report already says moderate → the Moderate obstructive apnea options page will fit better.
- If your report already says severe → go straight to the Severe obstructive apnea options page instead.
If you have central flags → start with the Central sleep apnea treatment options page.
"Central flags" means wording on your sleep study report — not how you feel — such as "central apnea," "CSA," "central events," "central apnea index (CAI)," or "Cheyne-Stokes respiration." "Mixed or complex flags" work the same way — look for report wording like "mixed apnea," "complex sleep apnea," or "treatment-emergent central apnea."
If you have mixed or complex flags → start with the Mixed sleep apnea treatment options page, since these often call for a specialist conversation anyway.
If you don't have your report in front of you, or you're not sure which wording applies, ask your clinician directly which bucket fits you.
Treatments by apnea type
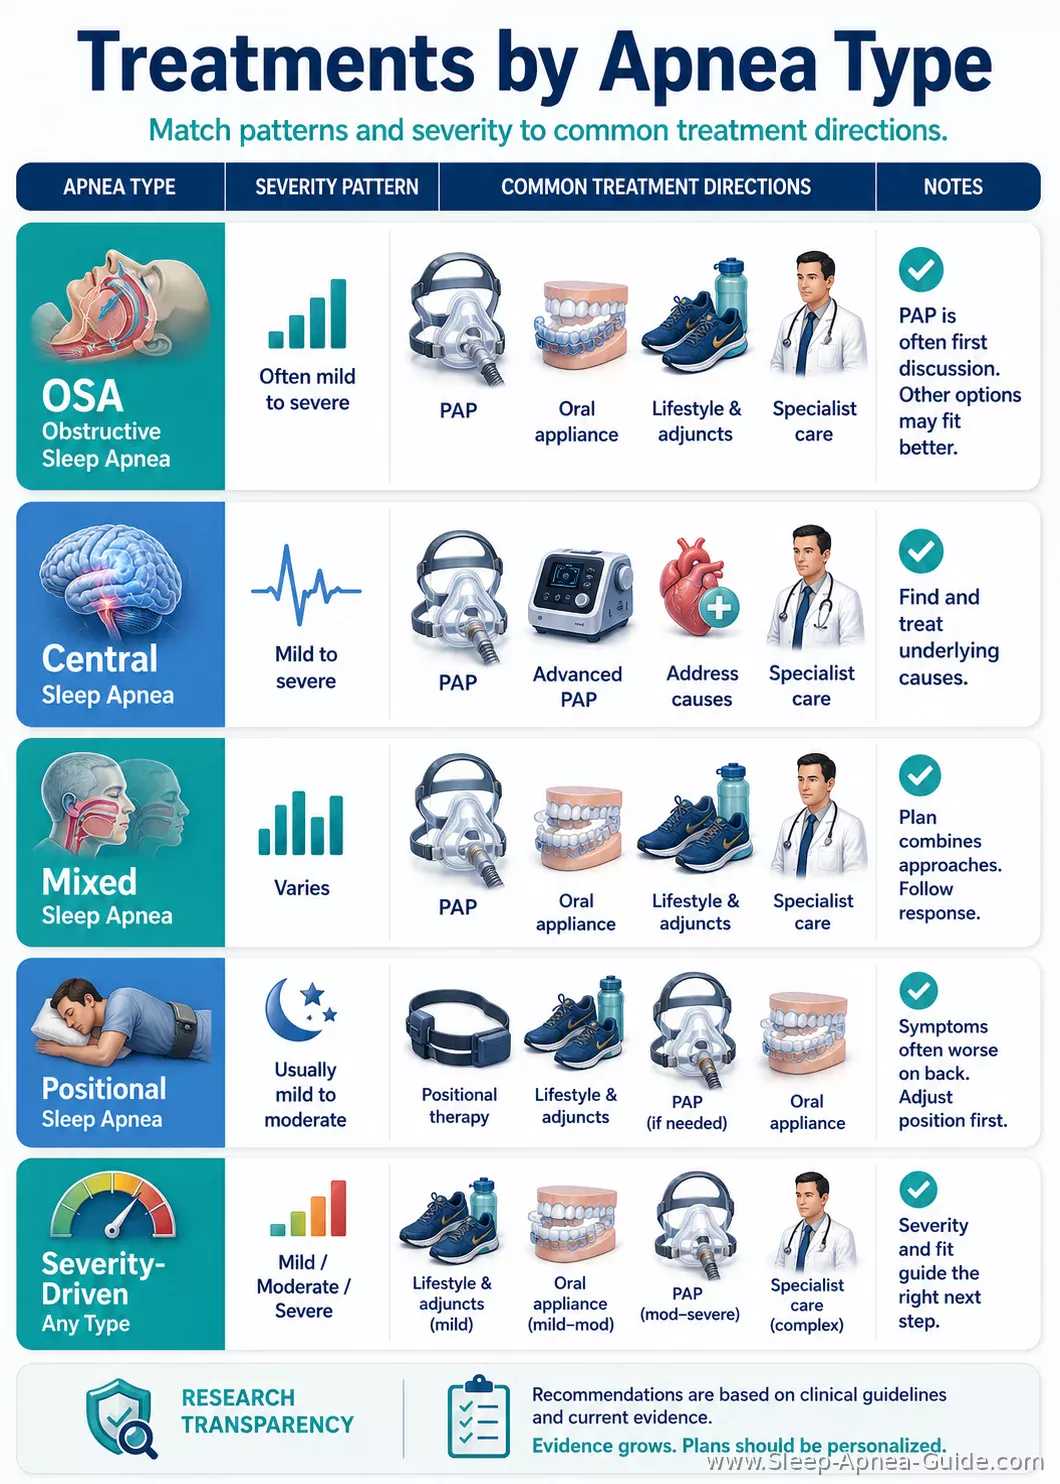
Matching treatment to your specific diagnosis is what makes a plan actually work. The table below is built to help you find your pattern and see what usually comes up first in that conversation with your clinician — not to tell you what to do, but to help you walk in prepared.
Find yourself here:
- If your report says obstructive (OSA), mild to moderate → PAP/CPAP is usually where the first conversation starts, with oral appliances often discussed as an alternative.
- If your report shows central flags → this usually points toward a specialist evaluation for advanced PAP options.
- If your report shows mixed or complex flags → standard CPAP may need adjustment, and a specialist evaluation for advanced PAP is common.
- If your report notes a positional pattern or REM-predominant events (mostly happening during dream sleep or in a specific sleep position) → positional therapy or targeted adjustments may come first. Studies commonly define positional obstructive sleep apnea as a supine AHI at least twice the non-supine AHI, one of the patterns that can make positional therapy part of the plan. [10] Research also suggests a total-night AHI can underestimate how much of the problem happens specifically during REM sleep, which can matter when symptoms are pronounced despite a lower overall AHI. [11]
- If your report shows notable oxygen drops (your lowest oxygen point, called the nadir, or time spent below 88%) → this often shapes urgency and machine settings, even within PAP. Research indicates the depth of oxygen desaturation and time spent below oxygen thresholds add information beyond event counts alone, part of how clinicians gauge urgency and follow-up needs. [12]
- If you're not sure which of these describes you yet → that's worth asking your clinician directly at your next visit.
This table reflects researched clinical patterns, not firsthand testing — always confirm what applies to you with your clinician.
To use this: scan for your report's wording, note what's commonly discussed first for that pattern, then use the "Where to go next" router earlier on this page to pick your starting page.
CPAP alternatives
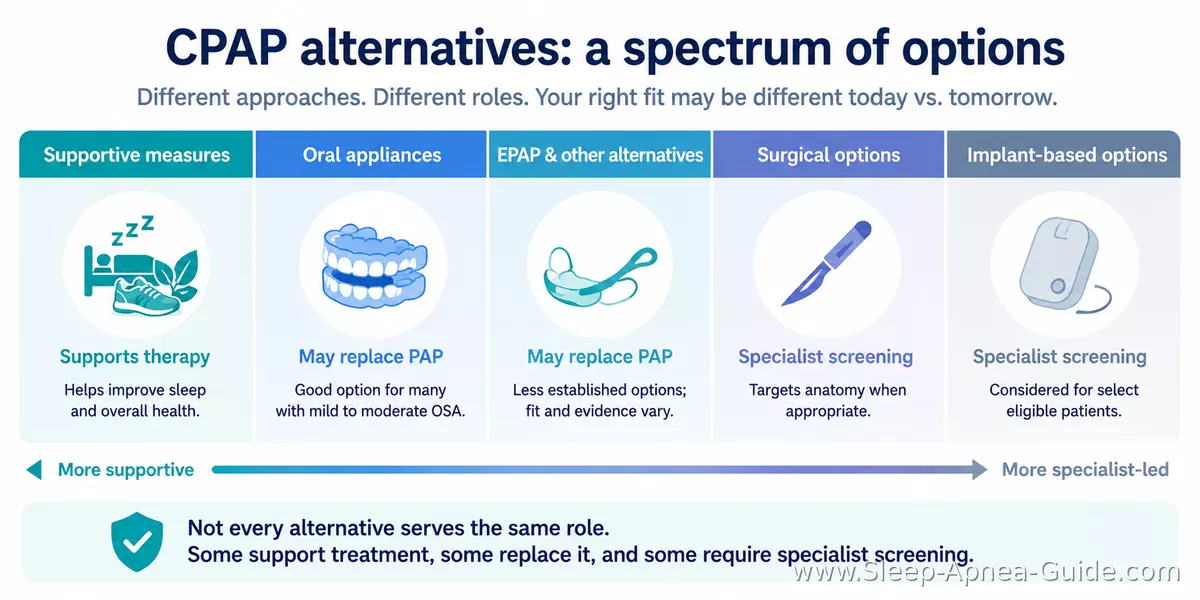
When you're exploring what else is out there, it helps to know whether an option supports your current treatment, could replace it, or means stepping up to specialist-led care.
- Extra support: helps your results alongside a primary therapy, without replacing it.
- Substitute: can be used instead of CPAP for some people, depending on diagnosis and severity — not a general replacement.
- Specialist escalation: typically needs screening or a workup, with a specialist guiding the decision.
Here's how the common options sort into those three buckets:
- Extra supports: positional therapy, weight loss, oropharyngeal (mouth and throat) exercises. A Cochrane review found positional therapy reduced both AHI and daytime sleepiness scores compared with no active treatment, while CPAP reduced AHI more than positional therapy did. [10] A meta-analysis of oropharyngeal exercises reported an average AHI reduction from about 24.5 to 12.3 events per hour in adults, alongside improvements in snoring and sleepiness — though most studies were small and focused on selected patients. [13]
- Substitutes: oral appliances, EPAP valves (small devices worn over the nostrils).
- Specialist-led substitutes: implant-based options, surgery.
Often worth troubleshooting first: mask fit or leaks, and pressure comfort (ramp settings).
Often worth discussing alternatives sooner: persistent intolerance even after adjustments, or central/mixed flags on your sleep study.
For the fuller "troubleshoot or switch" logic, scroll down to When to switch treatments, or start with CPAP troubleshooting.
Oral appliance therapy
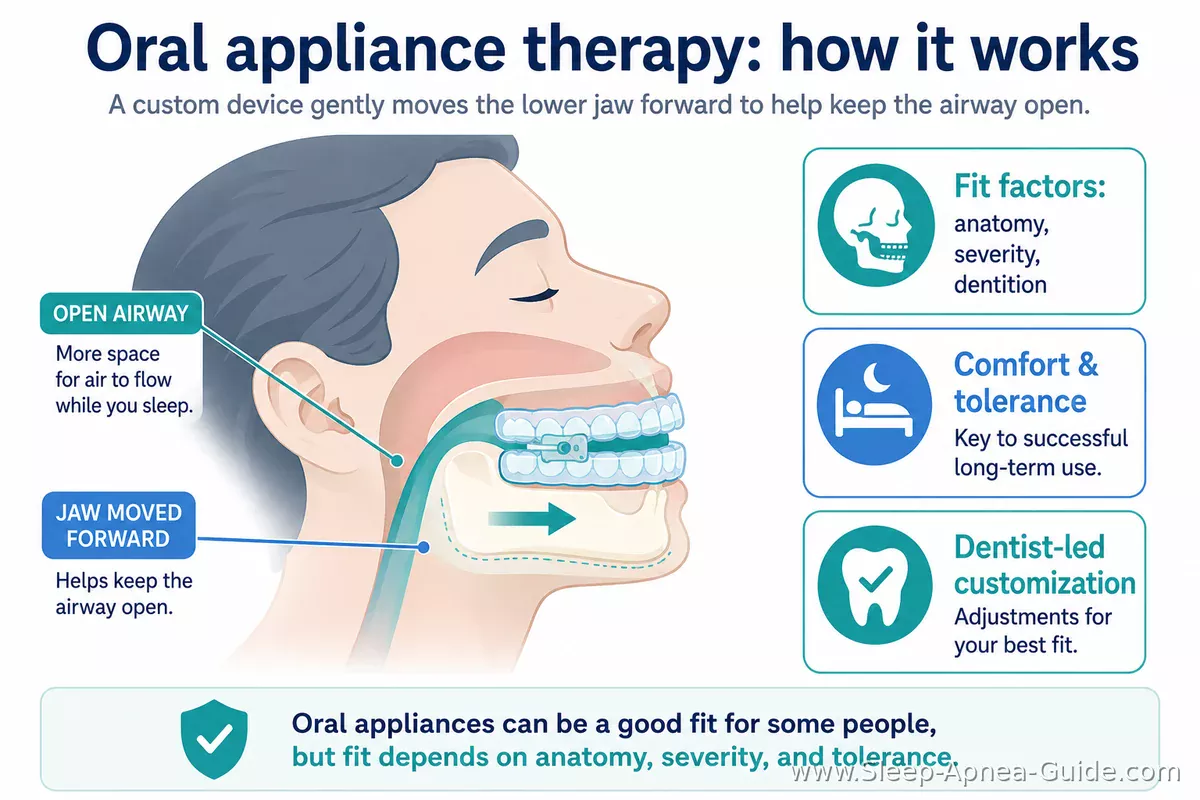
Dentist-led oral devices offer a different route for those comparing PAP therapy to other treatments for sleep apnea. These are commonly considered for mild to moderate OSA, for people who can't tolerate PAP, or when anatomy favors this kind of device.
- Who it tends to fit: Patients with mild-moderate OSA who want a less claustrophobic, highly travel-friendly alternative to CPAP. Guidelines support considering an oral appliance for adults with OSA who can't tolerate CPAP or who prefer a different therapy. [14]
- What to expect: You'll need dental customization, regular adjustments, and monitoring for possible dental or TMJ (jaw joint) side effects. Oral appliances generally reduce AHI less than CPAP in comparative studies, though some patients use them more consistently — a tradeoff that's part of why they remain a standard alternative for selected adults. [14]
- What to verify with your clinician: Confirm you're a good candidate. Check with both a sleep physician and a qualified dental sleep medicine specialist. Guidelines call for oversight by a qualified dentist to monitor dental side effects, along with follow-up with a sleep physician and repeat sleep testing to confirm the device is working. [14] In practice, candidacy also depends on the condition of your teeth and gums, any jaw-joint symptoms, and how far the jaw can comfortably move forward — checks that happen at the dental evaluation rather than from the sleep study alone. [15]
Learn more: Oral appliance detail.
Natural remedies for sleep apnea

It is completely valid to want to try low-risk, natural steps while also following your clinician's guidance for your sleep health.
When looking at lower-tech options, it is important to separate supportive steps from overhyped claims. Positional therapy, targeted weight loss, and oropharyngeal (mouth and throat) exercises have meaningful evidence behind them in certain cases. However, these are mainly supportive. They may help as extras depending on your severity and type, but they are rarely standalone fixes for moderate to severe OSA.
Avoiding alcohol close to bedtime and reviewing sedating medications with a clinician are commonly included in OSA management, since both can worsen airway collapsibility or how easily someone wakes during an event — though neither is presented in guidelines as a stand-alone treatment for moderate or severe OSA. [16]
Learn more: Positional therapy, or Lifestyle supportive steps (alongside your main treatment).
Does losing weight help sleep apnea?

Weight management is often recommended as part of a full treatment plan. Shedding pounds can significantly reduce the severity of obstructive events for many people. In one long-running study cohort, weight loss was associated with reduced OSA severity, while weight regained over time tracked with a return of symptoms — supporting weight as something that can shift the picture in either direction rather than a one-time fix. [17] Still, it is generally viewed as extra support within a broader treatment plan, not a guaranteed standalone cure.
Keep your expectations realistic. For newer weight-loss medications, direct evidence on OSA outcomes is still thinner than the evidence on weight loss itself, part of why these are usually framed as obesity treatment that may improve OSA burden, rather than as a stand-alone OSA therapy. [3] How much you improve varies a lot depending on your unique anatomy.
Always verify with your clinician when weight-management medications or bariatric surgery are being considered. Weight-loss medication can be considered for some adults with OSA and obesity when lifestyle changes alone haven't reached the target, using the same criteria applied to weight-loss medication generally. In one randomized trial, a GLP-1 medication paired with diet and exercise led to a greater reduction in AHI than diet and exercise alone, in adults with obesity and moderate-to-severe OSA who couldn't or wouldn't use CPAP. [3][18]
Learn more: Weight loss and sleep apnea.
When to switch treatments
Knowing when to fix your current setup, and when to ask about a different route, is vital.
Quick checkpoint (60 seconds) — answer yes or no:
- Have I tried adjusting my mask, headgear, or pressure settings with my clinician or equipment provider's guidance?
- Have I had a follow-up check-in about those adjustments? Guidance supports reassessment — including repeat sleep testing — when symptoms return, PAP data don't add up, or a non-PAP approach has been tried, rather than routine retesting for someone doing well. [12]
- Does my report flag central or mixed events, or notable oxygen drops?
If you answered yes to #3, that's worth prioritizing — bring it to your clinician first, since it may change the whole path. Not medical advice, just a sequencing hint.
Troubleshoot first if: you haven't yet worked through a baseline — fit, comfort, and pressure adjustments, plus a follow-up check-in — with your care team. Many comfort issues resolve somewhere in that process. Guidelines support educational, behavioral, and remote-monitoring support during PAP setup, part of why fit, comfort, and leak issues are usually addressed through troubleshooting before the plan itself is reconsidered. [1]
Discuss switching if: you've worked through that baseline and it still isn't working, or your report already flags something that changes the conversation. If you've made reasonable adjustments and it still feels unsustainable, that's not failure — it's data.
- Comfort or fit problems (leaks, irritation, claustrophobia) → Next step: Bring this up with your clinician or equipment provider — mask fit, headgear, and pressure settings are usually adjustable with their guidance.
- Clinical or report changes (central or mixed flags) → Next step: Ask your clinician about a referral for advanced PAP evaluation. When obstructive events improve on PAP but central-type events emerge or persist, that finding commonly shifts the conversation from routine mask or pressure troubleshooting toward central-event evaluation. [2]
- Life constraints (travel, irregular schedule) → Next step: Ask your clinician whether an oral appliance fits your routine better.
- Hard-stop intolerance (months of real effort, still can't tolerate CPAP) → Next step: Ask about an implant or surgical consultation.
Your diagnosis, severity, and personal comfort all matter deeply. Always verify your plans with a clinician.
If you're still in fix-mode, start with CPAP troubleshooting. If your report already flags something, or you've hit a hard stop, ask for a referral to a sleep specialist.
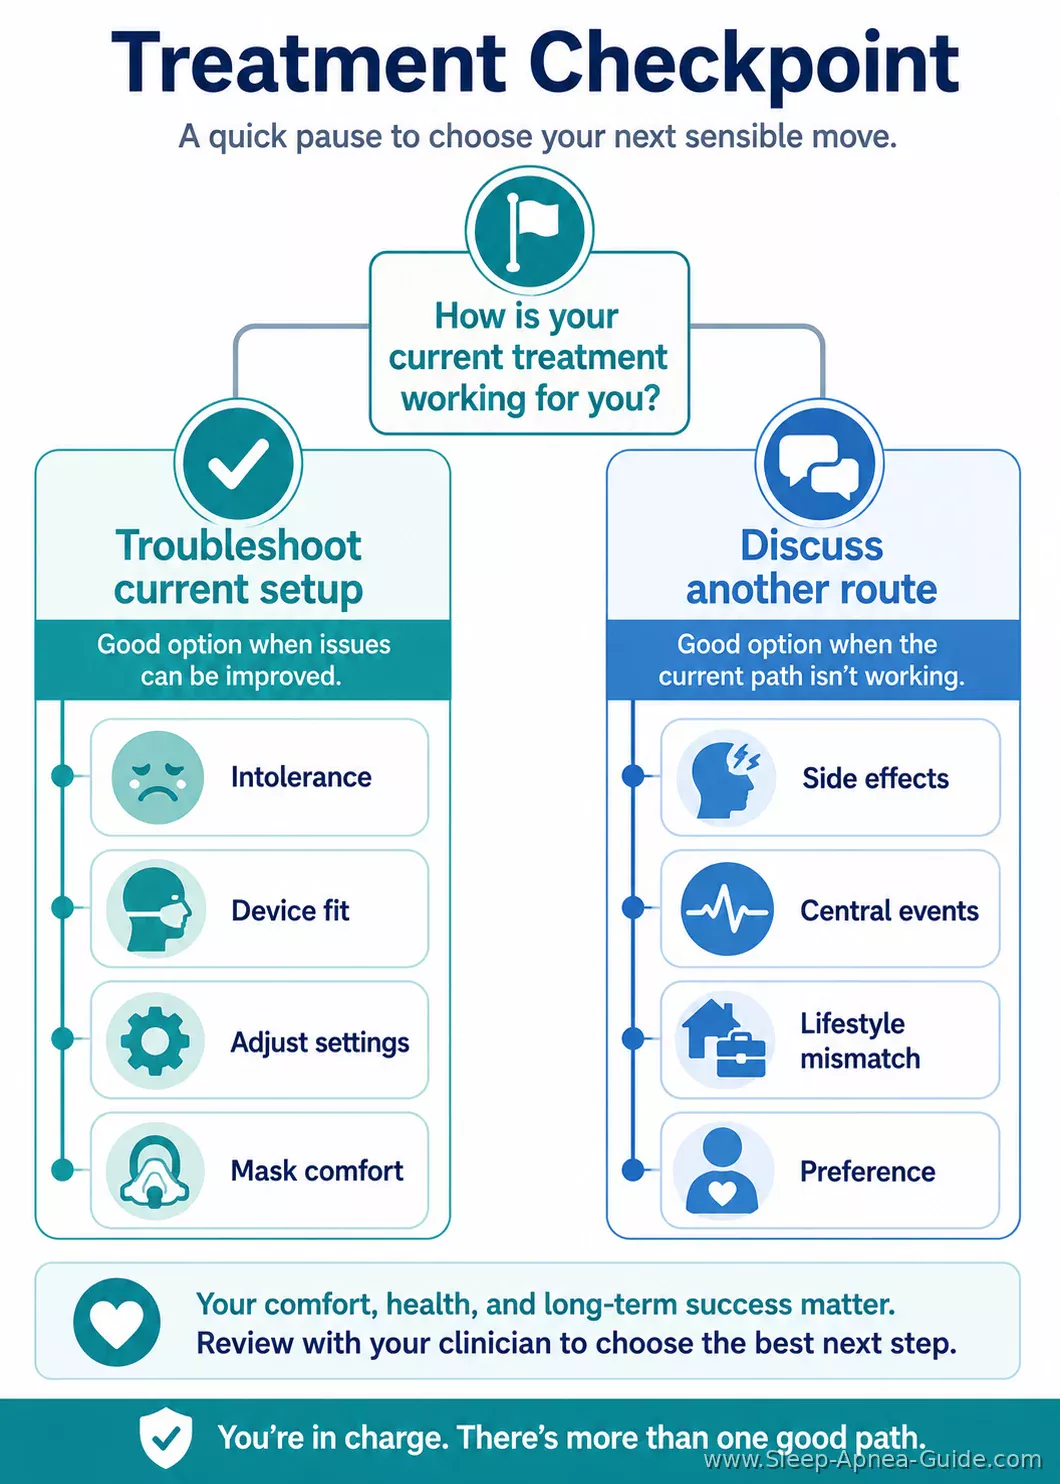
Remember, more than one issue can be true at once, and you do not need to solve everything today. Take your time, prioritize your comfort, and always verify treatment decisions with your clinician. Ready to take the next step? See how your pattern maps to treatment in Treatments by apnea type.
Sources:
- [1] American Academy of Sleep Medicine — Clinical practice guideline on PAP therapy for adults with obstructive sleep apnea. https://pubmed.ncbi.nlm.nih.gov/30736887/
- [2] Central sleep apnea evaluation and subtypes. https://pubmed.ncbi.nlm.nih.gov/23319967/
- [3] American Thoracic Society — Weight management guideline for OSA and obesity. https://pubmed.ncbi.nlm.nih.gov/30215551/
- [4] American Academy of Sleep Medicine — Surgical referral guideline for adult OSA. https://pubmed.ncbi.nlm.nih.gov/34351848/
- [5] Tonsillectomy in adult OSA. https://pmc.ncbi.nlm.nih.gov/articles/PMC3480570/
- [6] Palatal, tongue-base, and skeletal surgery review for OSA. https://pubmed.ncbi.nlm.nih.gov/24549887/
- [7] Inspire upper-airway stimulation — FDA indications and contraindications. https://professionals.inspiresleep.com/en-us/indications-and-contraindications/
- [8] Medicare coverage determination for hypoglossal nerve stimulation. https://www.cms.gov/medicare-coverage-database/view/lcd.aspx?LCDId=38276
- [9] remedē System — FDA approval summary for central sleep apnea. https://www.accessdata.fda.gov/cdrh_docs/pdf16/P160039B.pdf
- [10] Positional obstructive sleep apnea — definition and evidence. https://pubmed.ncbi.nlm.nih.gov/31041813/
- [11] REM-predominant obstructive sleep apnea and AHI measurement. https://pubmed.ncbi.nlm.nih.gov/27965139/
- [12] Oxygen desaturation and follow-up testing considerations in OSA. https://pubmed.ncbi.nlm.nih.gov/33704050/
- [13] Oropharyngeal exercise meta-analysis for OSA. https://pubmed.ncbi.nlm.nih.gov/25568716/
- [14] American Academy of Sleep Medicine and American Academy of Dental Sleep Medicine — Oral appliance therapy guideline. https://pubmed.ncbi.nlm.nih.gov/26094920/
- [15] Oral appliance candidacy factors. https://aadsm.org/docs/JDSM.2.2.77.pdf
- [16] National Heart, Lung, and Blood Institute — Sleep apnea treatment overview. https://www.nhlbi.nih.gov/health/sleep-apnea/treatment
- [17] Sleep AHEAD cohort — weight change and OSA severity. https://pubmed.ncbi.nlm.nih.gov/28532930/
- [18] SCALE Sleep Apnea trial — liraglutide for adults with obesity and OSA. https://pubmed.ncbi.nlm.nih.gov/27005405/
- Home
- Sleep Apnea Treatments
Affiliate Disclosure
As an Amazon Associate I earn from qualifying purchases.
Recent Articles


-
The Best CPAP Pillow For Sleep Apnea
Jul 22, 18 01:15 PM
 Why do you need a CPAP pillow, Which pillow is the best for CPAP users, and how to make one if you can't afford It.
-
How To Use Portable Pulse Oximeter To Track Sleep Apnea Treatment?
Jul 09, 18 02:51 PM
 How can a portable pulse oximeter help with CPAP treatment? Can you trust a pulse oximeter to monitor sleep apnea? Click here to find the answers.
-
The 3 Best Ways To Stop CPAP Dry Mouth
Jun 23, 18 11:02 AM
 How can you prevent and treat CPAP dry mouth? A practical guide to assist you with dry mouth when using the CPAP machine.
Subscribe
Don't worry - your e-mail address is totally secured. I promise to use it only to send you monthly updates with useful tips to improve you sleep apnea.


